Carematix solutions by program
What Changed for
RPM Reimbursement
in 2026?
For 2026, CMS continues to reimburse device setup, device supply and data transmission, and treatment management through remote patient monitoring solutions. Understanding how each code fits together helps practices build sustainable RPM solutions for providers and program models.

How RPM Works End-to-End
From data capture through clinical review and documentation—a complete integrated RPM solution designed to support scalable remote patient monitoring.
Physiologic Data Collection
Connected, FDA-cleared devices capture blood pressure, weight, glucose, and pulse oximetry readings outside the clinic - no manual transcription required.
Secure Data Transmission
Readings are automatically transmitted over a secure cellular connection to the monitoring platform, ensuring HIPAA-compliant data delivery.
Trend-Based Signal Analysis
The platform contextualizes raw measurements across time, filtering noise and surfacing clinically meaningful trends for the care team.
Clinical Review & Intervention
Care-team members review prioritized signals, communicate with patients, and escalate when thresholds are crossed - all within the clinical workflow.
Documentation & Billing Support
Every interaction is documented for continuity of care, and staff time is attributed to the appropriate billable service codes.
Turn RPM Data Into Clear Clinical Next Steps
Collecting patient readings is only the beginning. Carematix helps care teams understand changes over time, prioritize readings that may require attention, and follow up according to established clinical protocols—without overwhelming staff with unnecessary alerts.
Connect RPM Services to the Work Your Team Performs
Medicare's RPM reimbursement model has three areas of service: device set up and patient consent, capture and transmit physiologic data, and document treatment management. Review the code categories below to understand RPM program requirements.
Setup and education
Can be charged once per episode of care after 16 readings of data have been transmitted.
Published guide amounts and service requirements can vary by payer, locality, and program setup. Confirm current billing requirements with your compliance and revenue-cycle teams before submitting claims.
Estimate Your Annual Revenue Opportunity
See how a practice-owned RPM program could support proactive patient care while creating a sustainable new revenue opportunity. Adjust the number of eligible Medicare patients in your practice to explore estimated annual reimbursement.
Annual Revenue
99458
99458
Additional Medicare Services
Combine CCM and RPM for Better Connected Care
Eligible patients may receive both Chronic Care Management and Remote Patient Monitoring services during the same month. CCM supports care planning and coordination, while RPM uses transmitted physiologic data to support ongoing treatment management. Each service requires distinct, non-overlapping time entries and must be documented separately. No interaction may be counted toward both RPM management and CCM in the same billing month.

Billing CCM and RPM in the Same Month
When applicable billing code requirements are independently met, Chronic Care Management and Remote Patient Monitoring may be billed during the same calendar month. Carematix supports documentation of separate RPM and CCM activities.
CCM care coordination
Covers the initial 20 minutes per calendar month of clinical staff time directed by a physician or QHP for patients with multiple chronic conditions.
Can be billed concurrently with RPM when time is tracked separately.
Published guide amounts and service requirements can vary by payer, locality, and program setup. Confirm current billing requirements with your compliance and revenue-cycle teams before submitting claims.
Estimate Your Annual Revenue Opportunity
See how a practice-owned RPM and CCM program could support proactive patient care while creating a sustainable new revenue opportunity. Adjust the number of eligible Medicare patients in your practice to explore estimated annual reimbursement.
Annual Revenue
99458
99490
99439
Advanced Primary
Care Management
Support comprehensive, ongoing care without monthly time-tracking requirements. APCM provides a monthly care-management framework with payment tiers based on patient complexity and qualifying Medicare status.
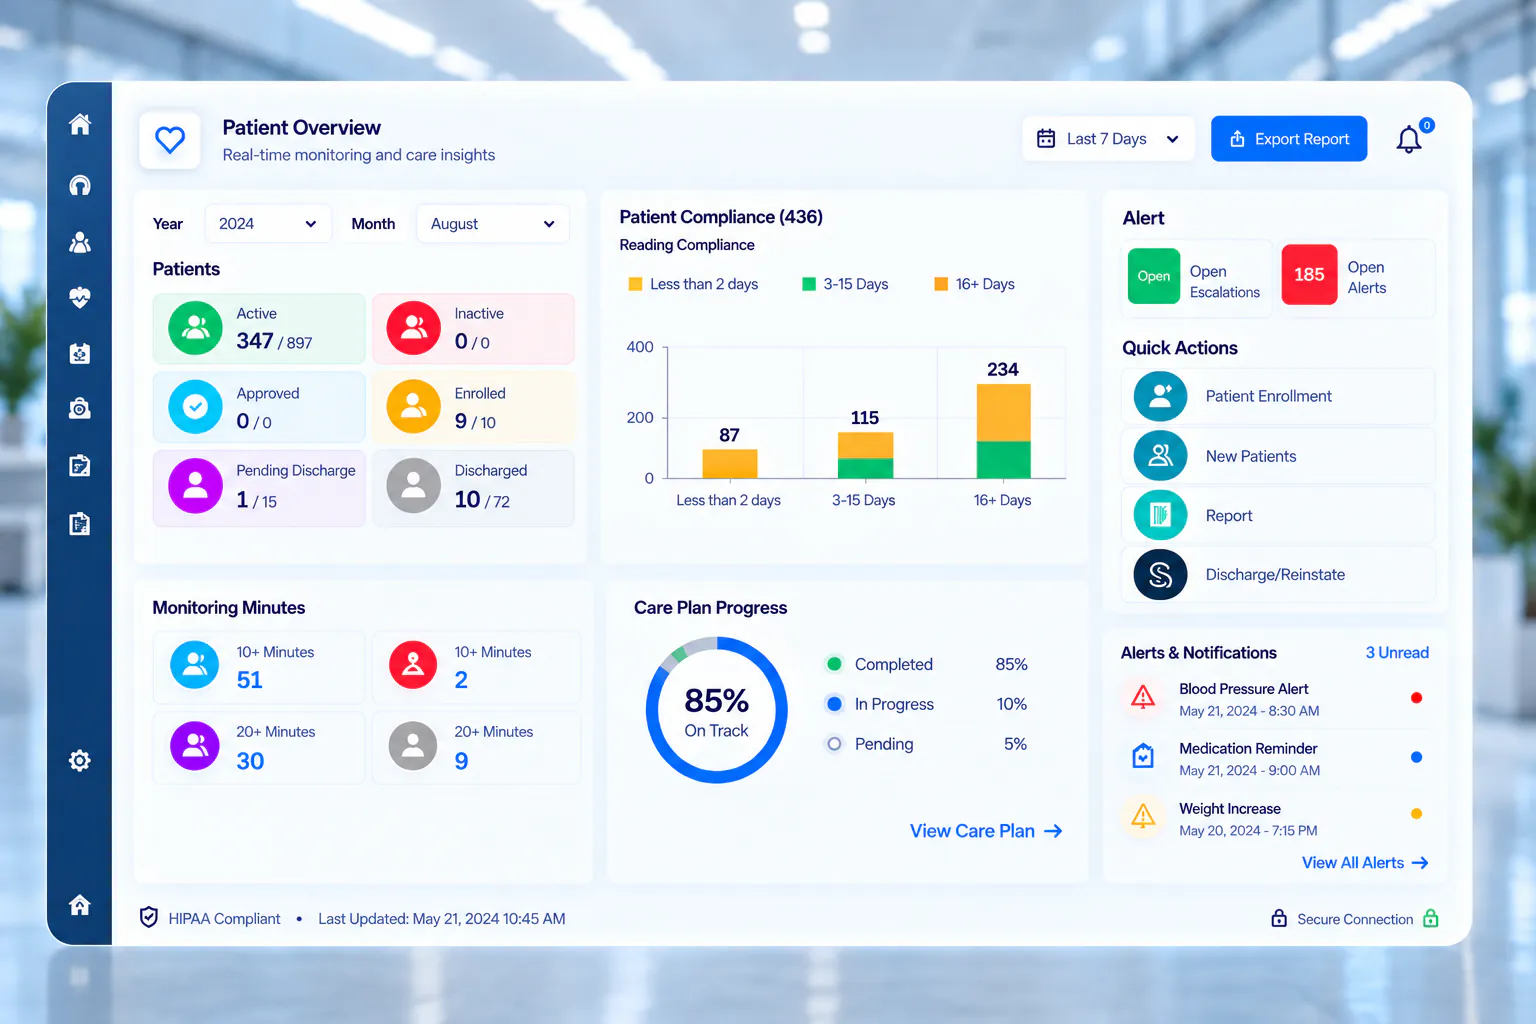
A Shift Beyond Time-Based Care Management
CMS introduced APCM to support comprehensive, ongoing primary care through a monthly payment structure that is based on patient complexity rather than accumulated staff time. Practices must meet applicable patient eligibility, service, access, documentation, and billing requirements.
No Monthly Time Threshold
Unlike time-based CCM codes, APCM does not require practices to document a minimum number of care-management minutes each month.
Complexity-Based
APCM includes three monthly billing codes—G0556, G0557, and G0558—based on the patient’s number of chronic conditions and, for the highest level, QMB status.
Billable with RPM
Patients may be enrolled in both APCM and RPM and practices can bill for both services in the same month. These codes are intended to support ongoing longitudinal care.
Comprehensive Ongoing Care
APCM supports ongoing primary care through care planning, care coordination, enhanced access, transitional care, and population-health management between scheduled visits.
Combine RPM and APCM Billing in the Same Month
RPM and APCM may be billed for the same patient during the same month when the requirements for each service are independently met. APCM supports longitudinal primary care, while RPM separately covers connected-device data collection and treatment management. The appropriate APCM level is selected based on the patient's chronic conditions and Medicare status, not time spent.
APCM Level 1
Monthly APCM services for a patient with zero or one chronic condition, provided under the direction of the patient's primary care provider.
Care plan on file and updated as medically necessary. Billed under primary care provider.
Published guide amounts and service requirements can vary by payer, locality, and program setup. Confirm current billing requirements with your compliance and revenue-cycle teams before submitting claims.
Estimate Your Annual Revenue Opportunity
See how a practice-owned RPM and APCM program could support proactive patient care while creating a sustainable new revenue opportunity. Adjust the number of eligible Medicare patients in your practice to explore estimated annual reimbursement.
Annual Revenue
99458
G0557
G0558
Connected Chronic
Disease Management for
Rural Health Transformation
Carematix delivers advanced technology solutions for Remote Patient Monitoring and Chronic Disease Management, helping you reach and engage every member of your community. Our platform supports cellular-enabled devices—including blood pressure monitors, weight scales, glucometers, and pulse oximeters—making it easy to collect real-time health data—no Bluetooth, apps, or home internet required. Improve access to care, empower patients, and stay connected through intuitive, consumer-friendly tools.

Advance Rural Healthcare In Your Community
Carematix enables rural health organizations to extend care into the community and patients' homes, helping providers connect with patients where they live. Our scalable Remote Patient Monitoring (RPM) solutions support diverse population needs through easy-to-use cellular-connected devices. From high-risk chronic disease patients to broader population health initiatives, Carematix helps organizations scale connected care and strengthen ongoing patient engagement.
By enabling earlier risk detection, improving care coordination, and strengthening chronic disease management, Carematix helps healthcare organizations improve outcomes while supporting sustainable RPM and APCM reimbursement opportunities, including CMS Rural Health Transformation initiatives.
By submitting this form, you agree to be contacted by Carematix regarding your inquiry.
Advancing Chronic Care in Rural America
Carematix helps rural health providers move from episodic care to continuous, connected health management. Our Remote Patient Monitoring (RPM) and Care Coordination platform empowers clinics to track and support patients with chronic conditions such as hypertension, diabetes, COPD, and heart failure — the leading drivers of preventable hospitalizations across rural Illinois. By extending care into the home, Carematix enables early intervention, improved adherence, and better long-term health outcomes, keeping rural residents healthier and reducing the need for costly hospital care.
Sustainable and Scalable Through Reimbursement
Carematix’s model is designed for sustainability. The platform integrates seamlessly with CMS reimbursement pathways, including Remote Physiologic Monitoring (RPM), Chronic Care Management (CCM), and Advanced Primary Care Management (APCM). These programs provide a recurring, payer-aligned funding mechanism that allows Rural Health Clinics to expand access and continuity of care without reliance on grant funding.
AI-Powered Support for Clinicians and Patients
Carematix leverages artificial intelligence to identify early warning signs, guide remote triage, and prioritize patients who need immediate attention. AI-powered clinical notes, intelligent alerts, and data trend analyses help clinicians focus time effectively, while patients receive personalized education and feedback that strengthen engagement and self-management.
Rural Workforce Empowerment
By enabling remote and team-based care, Carematix expands the reach of the rural clinical workforce. Providers, nurses, and care coordinators can monitor and manage patients from any location, reducing burnout, improving collaboration, and building long-term retention through flexibility and professional growth.
Interoperability and Data Integrity
Our cloud-based infrastructure connects securely to major EHRs using HL7, FHIR, and CCD standards, ensuring seamless data exchange while maintaining patient control over personal health information. This secure, transparent approach supports trust, compliance, and better-coordinated care across multiple care settings.
Driving Value-Based Outcomes
Carematix enables measurable improvements in chronic care management — fewer emergency visits, lower readmissions, and higher patient satisfaction. By supporting population health initiatives and aligning with value-based care goals, the platform helps rural communities thrive through healthier patients, stronger clinics, and sustainable care delivery.
Comprehensive Support for Rural Connected Care
From cellular-connected devices to flexible clinical workflows and available EHR integration, Carematix helps rural healthcare organizations extend chronic care beyond the walls of the clinic.
Pre-configured cellular devices require no Bluetooth, apps, or Wi-Fi, allowing rural patients to transmit readings with fewer technology barriers.
Combines Rural Health Transformation Program grants with recurring Medicare reimbursement to build sustainable care.
A web-based platform, configurable alerts, documentation tools to help care teams manage patient readings and outreach efficiently.
Timely access to blood pressure, weight, glucose, and oxygen readings helps care teams identify concerning trends and triage between visits.